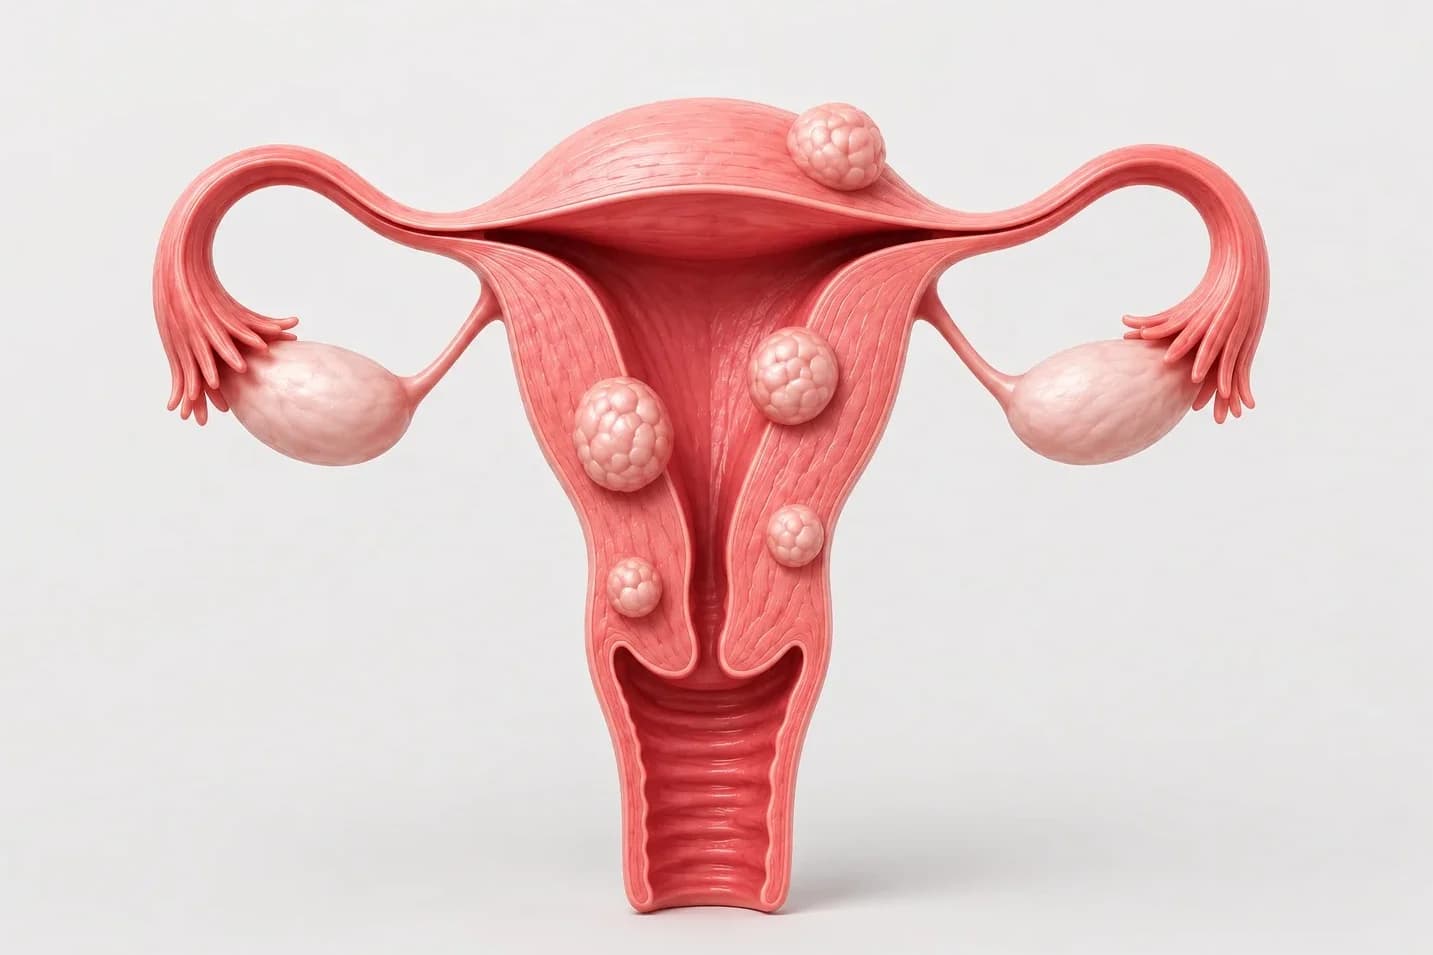
Reasons You Can't Get Pregnant: When Should You See a Doctor?


For many couples planning to have a baby, a pregnancy that takes longer than expected can be a source of worry. Comments from friends and family such as "We got pregnant in the first month" or "Just give it a little more time" can make that worry even worse. Yet, contrary to popular belief, pregnancy does not always happen within the first few months. Even in a healthy, fertile couple, the chance of conceiving in any given menstrual cycle is only about 20-25% on average. So not getting pregnant within a few months does not, on its own, mean there is a health problem.
That said, if pregnancy has not occurred after a certain period of regular, unprotected intercourse, a thorough evaluation of both partners becomes important. The reason a couple cannot conceive does not lie with the woman alone or with the man alone. Current research shows that roughly one third of infertility cases are due to female factors and one third to male factors, while in the remaining cases factors from both partners are present together or no clear cause can be identified.
The causes that affect the ability to conceive are wide-ranging. The most common include ovulation disorders, polycystic ovary syndrome (PCOS), endometriosis (chocolate cysts), problems with the fallopian tubes, diminished ovarian reserve, hormonal imbalances, sperm production disorders, genetic factors and lifestyle-related factors. In some couples, no clear cause can be found despite all investigations. This is called "unexplained infertility."
The good news is that, thanks to advances in reproductive medicine, many conditions that cause infertility can now be diagnosed early, and successful pregnancies can be achieved with personalized treatment plans. What matters most is being evaluated at the right time and avoiding unnecessary loss of time.
In this article, drawing on scientific evidence, we will look at the most common reasons for not getting pregnant, which tests are performed, and when you should see a reproductive health specialist.
1. Defining Infertility: What Is the 1-Year Rule?
Infertility, commonly referred to as "sterility" in everyday language, does not simply mean failing to get pregnant for a long time. Today, infertility is defined as the absence of pregnancy within the expected time frame despite regular, unprotected intercourse, or the need for medical assistance in order to conceive. This definition is also adopted by current international guidelines.
So why is waiting 1 year specifically recommended?
The main reason is that, biologically, the chance of pregnancy in any given month is limited. A woman develops only one egg per menstrual cycle, and after ovulation there is a very short window for fertilization. Although sperm cells can survive for a few days, the egg remains receptive to fertilization for only about 24 hours. That is why pregnancy is not expected every month, even in completely healthy couples.
Scientific studies show that about half of healthy couples conceive naturally within the first six months, and about 80-85% within the first year. For this reason, a detailed evaluation is recommended for women under 35 if pregnancy has not occurred after one year of regular, unprotected intercourse.
However, the picture changes with age. After 35 in particular, egg quality begins to decline along with egg numbers. The risk of chromosomal abnormalities in embryos rises while the chance of natural pregnancy steadily falls. For this reason, a six-month wait is considered sufficient for women aged 35 and over. After 40, time becomes even more precious, so women planning a pregnancy are advised to be evaluated without delay.
The table below summarizes the general approach:
| Woman's age | When to seek evaluation despite regular, unprotected intercourse |
|---|---|
| Under 35 | After 12 months |
| 35-39 | After 6 months |
| 40 and over | Evaluation recommended without waiting |
In some situations, however, it is not advisable to wait for these periods to pass, because the chance of pregnancy may decrease over time as the underlying condition progresses. For example, women with irregular periods, a previous diagnosis of chocolate cysts, past ovarian surgery, a history of chemotherapy or radiotherapy, or a risk of early menopause should be evaluated without delay. Likewise, in cases such as a severely reduced sperm count, previous testicular surgery, varicocele or a complete absence of sperm, it is important for the male partner to be evaluated early.
The most important point to remember is that infertility is not just a women's health issue. Today, evaluating the woman and the man together allows couples who are unable to conceive to reach a diagnosis faster and to have the most suitable treatment planned. An accurate evaluation early on can both improve the chance of natural pregnancy and, if needed, allow assisted reproductive treatment to begin on time.
2. The Most Common Obstacle in Women: Symptoms of Polycystic Ovary Syndrome (PCOS)
Polycystic ovary syndrome (PCOS), the most common cause of ovulation disorders in women, is a hormonal and metabolic condition that affects approximately 8-13% of women of reproductive age. Recent scientific studies show that the condition affects not only the ovaries but also metabolism, insulin balance and the hormonal system. For this reason, some international experts proposed the name "Polyendocrine Metabolic Ovarian Syndrome (PMOS)" to describe the condition more accurately, and with an article published in The Lancet in 2026, the term PMOS gained acceptance. In fact, the disease itself has not changed; it has simply been given a more accurate name.
Many women diagnosed with PMOS first worry, "Will I never be able to have children?" Yet this thought usually does not reflect reality. Although PMOS is a significant health condition that can reduce the chance of pregnancy, with appropriate treatment and timely intervention many women are able to achieve a healthy pregnancy, either naturally or with assisted reproductive treatment.
The core problem in PMOS is that the ovaries cannot develop eggs regularly and ovulation does not happen every month. In a normal menstrual cycle, the egg that develops each month ruptures out of its follicle once it reaches a certain maturity and passes into the fallopian tube. In PMOS, many small follicles start to grow, but most of them fail to mature, and ovulation may not occur. As a result, the meeting of egg and sperm needed for pregnancy is not possible every month.
This is why irregular periods are one of the most common symptoms in women with PMOS. Some women have a period only every two or three months, while in others menstrual bleeding becomes completely irregular. Even in women with regular periods, ovulation may not always occur. So having a period does not necessarily mean that ovulation is happening regularly.
Another key feature of PMOS is higher-than-normal levels of male hormones (androgens). This hormonal change can cause symptoms such as increased hair growth on the face, chin, chest or abdomen, acne, oily skin and, in some women, hair loss. Not every woman has all of these symptoms, and the severity of the condition varies from person to person.
It is also known that the condition is not limited to the reproductive system. A significant proportion of women with PMOS have insulin resistance. Insulin resistance causes the pancreas to secrete more insulin, and rising insulin levels in turn increase androgen production in the ovaries, which can make the ovulation disorder even more pronounced. For this reason, weight gain, fat accumulation around the waist and the risk of metabolic syndrome are also associated with PMOS. It should be remembered, however, that PMOS does not occur only in overweight women; it can also develop in women of normal weight.
A single blood test is not enough to diagnose PMOS. The diagnosis is made by evaluating the patient's history, menstrual pattern, physical examination findings, hormone tests and ultrasound together. Although seeing many small follicles in the ovaries on ultrasound supports the diagnosis, it is not sufficient on its own. Similarly, irregular periods alone or a polycystic appearance alone does not establish a diagnosis of PMOS. For this reason, the evaluation should always be carried out by an obstetrician-gynecologist.
The treatment plan is not the same for every woman. For women who are not planning to have children, the goal is to regulate the menstrual cycle and reduce metabolic risks, while for women who want to conceive, the main goal is to restore regular ovulation. To achieve this, lifestyle changes, weight control, ovulation induction or, where necessary, assisted reproductive techniques may be used.
In overweight women in particular, losing even 5-10% of body weight can markedly improve ovulation and increase the chance of natural pregnancy. A healthy diet, regular exercise and keeping insulin resistance under control are important parts of treatment.
For couples who have been unable to conceive for a long time because of PMOS, methods such as IUI (intrauterine insemination) or IVF (in vitro fertilization) may be considered. The choice of treatment is made by taking into account the woman's age, ovarian reserve, her partner's sperm characteristics and the duration of infertility together.
What You Should Know
Being diagnosed with PMOS does not mean you will not be able to have children. Today, thanks to personalized treatment, the majority of women with PMOS are able to achieve a successful pregnancy. What matters is being evaluated at the right time and also investigating any other underlying causes of infertility.
3. The Silent Obstacle: Does Endometriosis Prevent Pregnancy?
Some women live with severe period pain for years, accepting it as "normal," while in others a chocolate cyst is discovered during an ultrasound performed without any symptoms at all. This is exactly why endometriosis is often described as a "silent disease."
Endometriosis is a chronic, inflammatory disease in which tissue similar to the endometrium, which normally lines the inside of the uterus, settles outside the uterus. These lesions are most often found on the ovaries, the fallopian tubes, the back of the uterus and the lining of the abdominal cavity (peritoneum). When it settles inside the ovary, it forms cysts with dark brown contents over time, which is why it is commonly known as a chocolate cyst.
Endometriosis is estimated to affect about 1 in every 10 women of reproductive age, and it is seen much more often in women being evaluated for infertility. The reverse, however, is not always true: not every woman diagnosed with endometriosis is infertile. The extent of the disease, its location, ovarian reserve and the woman's age are the most important factors that determine the chance of pregnancy.
So how does endometriosis affect pregnancy?
There is no single answer to this question. The disease can affect the reproductive system through different mechanisms, and it does not progress the same way in every woman.
First of all, chocolate cysts that develop in the ovary can damage healthy ovarian tissue over time. This can lead to diminished ovarian reserve, especially with large cysts or in women who have had previous ovarian surgery. Diminished ovarian reserve, in turn, can affect the number of eggs that can be retrieved.
Endometriosis can also affect the fallopian tubes. Chronic inflammation and adhesions caused by the disease can impair the movement of the tubes or make it harder for sperm and egg to meet. In some patients, even when the tubes are fully open, they may not function normally because of the adhesions around them.
Another important effect is chronic inflammation in the abdominal cavity. Inflammatory substances released by endometriosis lesions are thought to have negative effects on the egg, the sperm and the developing embryo. For this reason, in some women, even if fertilization occurs, embryo development or implantation in the uterus may be adversely affected.
That said, the severity of the disease does not always go hand in hand with the chance of pregnancy. Some women with mild endometriosis can conceive naturally with ease, while patients with more advanced disease may need assisted reproductive treatment. For this reason, it is not right to make a definitive judgment about the chance of pregnancy based solely on an ultrasound image.
The table below summarizes the mechanisms through which endometriosis can affect pregnancy:
Structure affected by endometriosis | Possible effect on pregnancy |
|---|---|
| Ovary | Diminished ovarian reserve, negative impact on egg quality |
| Fallopian tubes | Harder for sperm and egg to meet |
| Peritoneum (abdominal lining) | Impaired movement of the reproductive organs due to adhesions and inflammation |
| Area around the uterus | Inflammatory changes that may affect embryo implantation |
One of the questions women diagnosed with endometriosis most often ask is whether they need surgery. The approach to this has changed considerably compared with years past. Whereas many chocolate cysts used to be operated on, current scientific guidelines do not recommend routine surgery for every patient.
Especially for women planning a pregnancy, the treatment decision should be made by considering the patient's age, ovarian reserve, cyst size, pain symptoms, previous surgeries and the duration of infertility together. While surgery is beneficial in some cases, removing more ovarian tissue than necessary can reduce ovarian reserve. This is why a personalized treatment plan is so important.
For many women diagnosed with endometriosis, the most important message is this: This disease does not mean you will not be able to have children. Today, thanks to natural conception, ovulation induction, IUI and IVF, many women with endometriosis are able to have a healthy pregnancy. Which method is most suitable should be decided by taking into account not only the stage of the disease but also the woman's age, ovarian reserve and factors related to her partner.
What You Should Know
The possibility of endometriosis should always be considered in women who experience severe period pain, pain during intercourse, chronic pelvic pain or unexplained infertility. Early diagnosis can improve quality of life and also help with more accurate pregnancy planning.
4. Hormone Tests: What Do AMH, FSH and LH Levels Tell Us?
Hormone tests are among the first evaluations performed for couples planning a pregnancy. In women in particular, hormones such as AMH, FSH and LH provide important information about how the ovaries are working. However, what these tests actually show is often misunderstood. Online, it is easy to come across claims with no scientific basis, such as "If your AMH is low, you can't get pregnant" or "If your FSH is high, IVF is your only option."
In reality, no hormone test on its own shows whether a woman can or cannot have children. These tests only offer guidance about ovarian reserve, ovulatory function and treatment planning. The final decision is made by evaluating them together with the woman's age, ultrasound findings, menstrual pattern, ovarian reserve, the condition of the tubes and her partner's semen analysis.
AMH Test: One of the Strongest Clues About Ovarian Reserve
In recent years, one of the most commonly used tests in infertility evaluation has been the Anti-Müllerian Hormone (AMH) test. AMH is a hormone secreted by the small follicles in the ovaries, and it provides information about ovarian reserve.
Women are born with a set number of eggs, and this number naturally declines with age. AMH levels generally fall in parallel with this decline. That is why AMH is considered an important biomarker for assessing ovarian reserve.
However, a common misunderstanding needs to be corrected here. AMH is not a pregnancy test. In other words, it cannot be said that a woman with a low AMH level will be unable to conceive naturally. Likewise, a high AMH level does not mean that pregnancy is guaranteed.
In fact, the most important use of AMH is to predict how the ovaries are likely to respond to medication, particularly in patients for whom IVF treatment is planned. Women with low AMH levels can be expected to produce fewer eggs. However, the quality of the eggs retrieved can be very good, especially in younger women, and healthy pregnancies can be achieved.
Conversely, although high AMH levels often suggest a good ovarian reserve, in some women they may be associated with polycystic ovary syndrome (PCOS). So high AMH is not always an advantage; the risk of an excessive ovarian response must also be taken into account when planning treatment.
FSH Test: Shows How Much Stimulation the Ovaries Need
FSH (follicle-stimulating hormone) is one of the key hormones secreted by the pituitary gland in the brain that keep the ovaries working. It rises at the start of each menstrual cycle and initiates egg development.
As ovarian reserve declines, the brain tries to stimulate the ovaries more strongly, and as a result FSH levels may rise. For this reason, a high FSH level, especially when measured on day 2 or 3 of the period, may be a sign of diminished ovarian reserve.
That said, FSH levels can vary from month to month. Moreover, some women may have diminished ovarian reserve despite normal FSH levels. That is why FSH is no longer evaluated on its own today; it is interpreted together with AMH and the antral follicle count seen on ultrasound.
The Relationship Between LH and Ovulation
LH (luteinizing hormone) is the hormone that triggers ovulation. Its sudden surge in the middle of the menstrual cycle (the LH surge) causes the mature egg to be released and pass into the fallopian tube.
In women with PCOS in particular, LH levels may be higher than normal and the balance between LH and FSH may be disrupted. This hormonal change can prevent regular ovulation. However, a high LH level alone does not establish a diagnosis of PCOS either. The diagnosis should be made together with clinical findings and other tests.
Why Are Hormone Tests Evaluated Together?
Reproductive hormones do not work independently of one another. Each one assesses a different aspect of ovarian function. For this reason, drawing conclusions from a single result can be misleading.
The table below summarizes what the most commonly used hormone tests assess.
| Hormone test | What does it tell us? |
|---|---|
| AMH | Ovarian reserve and the expected ovarian response to treatment |
| FSH | How much stimulation the ovaries need, and indirect information about reserve |
| LH | The ovulation mechanism and hormonal balance |
| Estradiol (E2) | Ovarian activity and follicle development |
| TSH | Thyroid function and reproductive health |
| Prolactin | Can suppress ovulation when elevated |
Do Hormone Tests Alone Show Your Chance of Pregnancy?
The answer to this question is 'no'.
There is no single test that determines a woman's chance of pregnancy. Age, egg quality, ovarian reserve, tubal patency, the structure of the uterus, sperm quality and overall health must all be evaluated together. For example, a 32-year-old woman with a low AMH level and a 42-year-old woman with the same AMH level do not have the same chance of pregnancy. This is because age plays a decisive role, particularly in egg quality and in the likelihood of embryos being chromosomally normal.
The purpose of hormone tests, therefore, is not to say "you can get pregnant" or "you can't," but to help create the most suitable treatment plan for each person.
Thanks to advances in assisted reproductive techniques in recent years, many women with low ovarian reserve are able to achieve successful pregnancies, and in patients with PCOS, regular ovulation can be restored with appropriate treatment planning. For this reason, rather than evaluating laboratory results in isolation, the best approach is for a reproductive health specialist to interpret the whole clinical picture together.
What You Should Know
AMH, FSH and LH levels do not, on their own, determine the likelihood of pregnancy. These tests provide information about the current state of the ovaries and are used as a guide in treatment planning. The most accurate assessment is possible when hormone tests, ultrasound findings, age and other infertility factors are considered together.
5. The Male Factor: Why Do Sperm Count and Motility Decline?
Although the evaluation of couples who cannot conceive often starts with the woman, current scientific evidence shows that the male factor plays a role, either alone or together with a female factor, in about half of all infertility cases. For this reason, the evaluation of couples who are unable to conceive should always begin by examining both the woman and the man together.
One of the most common causes of male infertility is a disorder of sperm production. However, a low sperm count is not the only problem. For pregnancy to occur, sperm need not only to be present in sufficient numbers but also to move well and have a normal structure. Another issue that has gained increasing importance in recent years is sperm DNA integrity.
Why Does Sperm Quality Decline?
Sperm production is a very delicate process and can be affected by many factors. Genetic diseases, hormonal disorders, past infections, testicular trauma or certain congenital problems can reduce sperm production. In addition, everyday habits have a greater effect on sperm quality than we might think.
In particular, smoking, excessive alcohol consumption, obesity, a sedentary lifestyle, a poor diet and chronic stress can negatively affect sperm count, motility and morphology. Prolonged exposure to high temperatures, certain chemicals and environmental toxins are also among the factors that can disrupt sperm production.
One of the most important treatable causes of male infertility is varicocele. This condition, defined as the enlargement of the veins of the testicle, can raise testicular temperature and negatively affect sperm production. Not every varicocele needs treatment, but in suitable patients surgical treatment can improve sperm parameters.
Age matters not only for women but for men too. Although men continue to produce sperm throughout their lives, the rate of sperm DNA damage can increase with age, and this can affect embryo development.
The Semen Analysis Is the First and Most Important Step
The first-line test in evaluating male infertility is the 'spermiogram (semen analysis)'. This test evaluates sperm count, motility, morphology (shape), semen volume and other basic parameters.
A semen analysis provides very valuable information about male reproductive health. However, there is one important point to keep in mind: A normal semen analysis result does not always mean that the sperm are completely healthy.
This is because a standard semen analysis evaluates the outward appearance and movement of the sperm cell but cannot show its genetic material.
Why Is Sperm DNA Damage Important?
Studies in recent years have shown that sperm DNA integrity plays an important role in achieving pregnancy and in embryo development. In some men, there may be breaks in the sperm DNA even though sperm count and motility are completely normal.
When sperm DNA damage is high:
- fertilization success may decrease,
- embryo development may be adversely affected,
- the likelihood of obtaining good-quality embryos may fall,
- the risk of pregnancy loss may increase.
For this reason, particularly in cases of repeated IVF failure, unexplained infertility or recurrent pregnancy loss, a Sperm DNA Fragmentation Test may be requested in addition to a standard semen analysis.
Of course, this test is not necessary for every patient. The decision to test should be made by evaluating the couple's history together with other findings.
Can Lifestyle Changes Affect Sperm Quality?
Sperm production is a process that takes about 70-90 days. For this reason, the effects of positive lifestyle changes begin to show after a few months.
A balanced diet, regular exercise, maintaining a healthy weight, quitting smoking and limiting alcohol consumption can all have a positive effect on sperm health. Keeping chronic conditions under control and avoiding unnecessary medication are also important.
However, not every sperm problem can be fixed with lifestyle changes. In particular, genetic diseases, hormonal disorders or serious production problems originating in the testicles may require further evaluation and appropriate treatment planning.
Why Is Early Evaluation Important in Male Infertility?
Although many people believe that the inability to have children is usually due to the woman, this is not true. Evaluating the male factor early both prevents unnecessary loss of time and makes it easier to plan the right treatment.
For some men, lifestyle changes alone are enough, while other patients may need medication, varicocele surgery or assisted reproductive techniques. In patients with no sperm at all (azoospermia), it may be possible to retrieve sperm from the testicle using microsurgical methods.
Today, thanks to the advanced techniques used in embryology laboratories, successful fertilization and pregnancy can be achieved even in patients with very few sperm. So finding a problem in a semen analysis does not mean that having children is impossible.
What You Should Know
When evaluating couples who cannot conceive, examining only the woman is not enough. A simple semen analysis is one of the most important steps in identifying the cause of infertility and allows many couples to reach a diagnosis quickly.
6. When Should You See a Reproductive Health Specialist?
Many couples planning a pregnancy are unsure how long they should wait. Yet an evaluation at the right time can both improve the chance of natural pregnancy and, if needed, allow treatment to begin without delay.
If any of the following situations apply to you or your partner, it is advisable to see a reproductive health specialist:
| Situation | Specialist evaluation recommended |
|---|---|
| Under 35 and no pregnancy after 1 year | ✓ |
| 35 or over and no pregnancy after 6 months | ✓ |
| Planning a pregnancy at 40 or over | Without waiting |
| Irregular periods or ovulation problems | ✓ |
| Diagnosis of endometriosis (chocolate cyst) | ✓ |
| Low AMH or a history of ovarian surgery | ✓ |
| History of recurrent miscarriage | ✓ |
| Abnormal sperm count or motility | ✓ |
| History of chemotherapy or radiotherapy | ✓ |
Early evaluation is important not only for starting treatment, but also for avoiding unnecessary loss of time and determining the most suitable roadmap for each person.
Conclusion
Not getting pregnant does not always mean infertility. However, if pregnancy has not been achieved within the expected time despite regular, unprotected intercourse, the underlying causes need to be investigated. Ovulation disorders, polycystic ovary syndrome, endometriosis, hormonal imbalances and male factor problems are among the most common causes of infertility.
Today, thanks to advanced diagnostic methods, most of these causes can be detected early and personalized treatment plans can be created. An evaluation at the right time can both improve the chance of natural pregnancy and, where necessary, allow assisted reproductive treatment to start without losing time.
It should be remembered that infertility is a couple's issue that requires the woman and the man to be evaluated together. Going through the evaluation process together helps reach a diagnosis sooner and plan the most suitable treatment.
Every couple's story is different. For this reason, rather than evaluating laboratory results in isolation, the best approach is to consider age, ovarian reserve, sperm characteristics, medical history and other clinical findings together. With early consultation, an accurate diagnosis and personalized treatment planning, many couples today are able to realize their dream of a healthy pregnancy.
Frequently Asked Questions
I can't get pregnant. When should I see a doctor?
For women under 35, an evaluation is recommended if pregnancy has not occurred within 12 months despite regular, unprotected intercourse. For women aged 35 and over, this period is 6 months. However, in situations such as irregular periods, endometriosis, low ovarian reserve or a known sperm problem, you should see an obstetrician-gynecologist or a reproductive health center without waiting for this period to pass.
What is the most common reason for not getting pregnant?
In women, the most common cause is ovulation disorders, particularly polycystic ovary syndrome (PCOS). In men, abnormalities in sperm count, motility or structure are the main factors. In addition, endometriosis, tubal problems, hormonal disorders and unexplained infertility can also affect the chance of pregnancy.
Does low AMH prevent pregnancy?
No. A low AMH level indicates diminished ovarian reserve, but it does not completely eliminate the possibility of natural pregnancy. Healthy pregnancies can occur with low AMH, especially in younger women. AMH is mainly a test that provides information about how the ovaries will respond to treatment.
Can women with polycystic ovary syndrome get pregnant naturally?
Yes. PCOS can make ovulation more difficult, but thanks to appropriate lifestyle changes, ovulation induction and, when necessary, assisted reproductive methods, many women are able to conceive either naturally or with treatment.
Does a chocolate cyst always cause infertility?
No. Not every patient with endometriosis experiences infertility. The extent of the disease, ovarian reserve, the woman's age and other reproductive factors are the most important factors in determining the chance of pregnancy.
Is a normal semen analysis result enough to have a child?
A semen analysis is the first step in evaluating male infertility. However, in some cases, even when sperm count and motility are normal, there may be impaired sperm DNA integrity. Further tests may be needed, especially in situations such as repeated IVF failure or unexplained infertility.
Why does the chance of pregnancy decrease with age?
As women age, not only the number of eggs but also egg quality declines. Especially after 35, the likelihood of chromosomal abnormalities in embryos increases while the chance of natural pregnancy steadily falls. For this reason, women planning a pregnancy at an older age are advised to be evaluated without losing time.
Does a man's age also affect fertility?
Yes. Although men continue to produce sperm throughout their lives, sperm DNA damage may increase with age. This can negatively affect embryo development and pregnancy success.
Specialist's Note
In infertility evaluation, decisions are not made based on a single test or a single laboratory result. The woman's age, ovarian reserve, ovulation status and the structure of the uterus and tubes should be evaluated together with the man's sperm characteristics. Today, thanks to personalized treatment, many couples are able to achieve a successful pregnancy.
Last updated: